From male-factor infertility to testosterone deficiency, Professor Vaibhav Modgil’s work highlights why men’s reproductive health deserves more attention—and why the right diagnosis matters as much as the treatment.
For many couples struggling to conceive, fertility investigations can quickly become focused on the woman. Male fertility, meanwhile, may receive less attention than it deserves. Yet male factors contribute to a substantial proportion of infertility cases, making the investigation of male reproductive health an essential part of the fertility journey.
Professor Vaibhav Modgil, a consultant urological surgeon and andrologist based in Manchester, works in this often-overlooked area of medicine. His clinical interests include male infertility, testosterone deficiency, erectile dysfunction and other conditions affecting men’s sexual and reproductive health. He is also associated with research into advancing evidence-based andrology and men’s health.
Modgil’s work brings attention to a subject that is frequently misunderstood: male fertility is not simply a question of whether a man can produce sperm. Hormones, sexual function, underlying medical conditions and the treatments prescribed for them can all influence reproductive health.
A recent review supervised by Modgil, Update on testosterone deficiency and therapeutic options for testosterone replacement therapy, published in Nature Reviews Urology in October 2026, examines how testosterone deficiency should be diagnosed and treated. While the review is not exclusively about infertility, it raises an important issue for men who hope to have children: treating low testosterone and preserving fertility are not always the same thing.
Understanding the relationship between testosterone and fertility
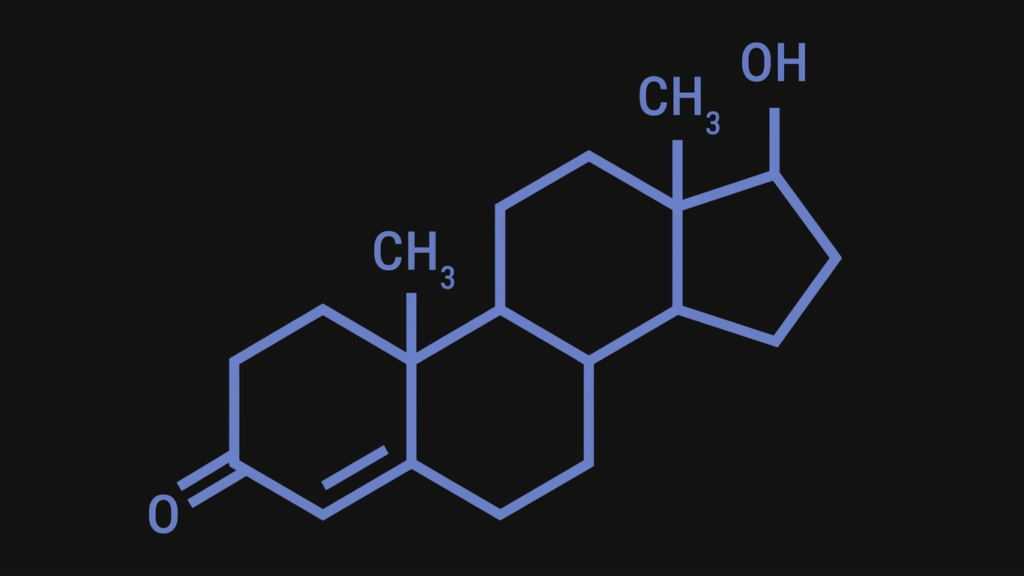
Testosterone is central to male sexual development and health. It contributes to libido, muscle and bone health, red blood cell production and several aspects of physical and psychological well-being. Low testosterone, also known as testosterone deficiency or male hypogonadism, can cause symptoms such as reduced sexual desire, fatigue, low mood and changes in body composition.
But testosterone’s relationship with fertility is more complicated than it might appear.
Sperm production depends on a coordinated hormonal system involving the hypothalamus, pituitary gland and testes. The brain releases signals that stimulate the pituitary gland to produce luteinising hormone (LH) and follicle-stimulating hormone (FSH). LH stimulates the testes to produce testosterone, while FSH works alongside testosterone within the testes to support sperm production.
This distinction matters because the testosterone measured in a blood test is not the same as the testosterone environment inside the testes. The testes need high local concentrations of testosterone to support normal sperm production.
Consequently, a man may have low testosterone and impaired fertility because of an underlying hormonal or testicular problem. In other cases, a man may have symptoms associated with low testosterone but still produce sperm. The two conditions can overlap, but they are not interchangeable.
That is why fertility assessments need to look beyond a single hormone measurement.
When treatment for low testosterone can affect fertility
Testosterone replacement therapy (TRT) is used to treat men with appropriately diagnosed testosterone deficiency. Depending on the individual, treatment may involve gels, injections, oral preparations or other formulations.
For men with confirmed deficiency, treatment can improve certain symptoms, including sexual desire, body composition and aspects of quality of life. However, the decision to prescribe testosterone requires particular care when a man wants to conceive.
Testosterone taken from an external source can suppress the brain’s release of the hormones that stimulate the testes. As LH and FSH levels fall, the testes may produce less of their own testosterone and sperm production can decline. In some men, sperm counts can become extremely low or sperm may no longer be detectable in the ejaculate.
This is one of the most important considerations in managing testosterone deficiency in men of reproductive age.
A man might begin treatment hoping to improve his energy, libido or sexual performance, without realising that the medication could undermine his immediate fertility goals. Men who are trying to conceive, or who may want children in the future, should discuss this with their clinician before starting treatment. Depending on the cause of the deficiency, alternative approaches may be considered to stimulate the body’s own testosterone production while better preserving sperm production. These options are not suitable for everyone and require specialist assessment.
The central message is straightforward: a treatment that improves one aspect of male health can affect another. Fertility intentions need to be part of the conversation from the beginning, rather than addressed only after a problem emerges.
Male infertility needs investigation, not assumptions
Infertility is often treated as a problem that can be understood from a single test result. In reality, male fertility assessments can involve several factors, and the appropriate investigations depend on the individual.
A semen analysis is a key starting point. It examines characteristics such as sperm concentration, movement and shape. However, a semen analysis alone does not always explain why a couple is struggling to conceive, and a result outside the reference range does not automatically mean that conception is impossible.
Medical history, previous illnesses or surgeries, medications, sexual function and examination findings can all help guide further investigation. Hormone tests may be useful in selected men, particularly when there are signs of hormonal deficiency, reduced sperm production or other relevant clinical findings.
Possible contributors to male infertility include hormonal disorders, problems with sperm production or transport, certain genetic conditions, previous testicular injury, and varicoceles—enlarged veins within the scrotum that can affect some men’s fertility. Lifestyle and general health may also be relevant, although their importance varies from one individual to another.
This is why specialist assessment matters. The objective is not merely to establish whether sperm are present, but to understand what might be affecting fertility and which interventions, if any, could help.
Recognising the signs of testosterone deficiency
Low testosterone does not always announce itself clearly. Some men experience changes in sexual desire or erections, while others notice persistent fatigue, reduced strength, low mood or a decline in their general sense of well-being. These symptoms can also have other causes, including poor sleep, depression, medication effects and chronic medical conditions.
The review supervised by Modgil emphasises the importance of combining clinical symptoms with biochemical evidence. A diagnosis should not be made simply because a man feels tired or because one blood test returns a low result.
Testosterone levels vary during the day, which is why testing is generally performed in the morning. A low result may need to be repeated, and additional investigations may be required to determine whether the cause lies in the testes, the hypothalamus and pituitary gland, or broader health factors.
The ADAM questionnaire: 10 questions that can help identify symptoms
The ADAM questionnaire, short for Androgen Deficiency in the Aging Male, is a screening tool designed to identify symptoms that may be associated with low testosterone. It asks men to answer yes or no to the following 10 questions.
- Do you have a decrease in libido (sex drive)?
- Do you have a lack of energy?
- Do you have a decrease in strength and/or endurance?
- Have you lost height?
- Have you noticed a decreased enjoyment of life?
- Are you sad and/or grumpy?
- Are your erections less strong?
- Have you noticed a recent deterioration in your ability to play sports?
- Are you falling asleep after dinner?
- Has there been a recent deterioration in your work performance?
How to interpret the answers
The screening result is considered positive if a man answers “yes” to question 1 or question 7, or answers “yes” to at least three of the other eight questions.
A positive result does not confirm testosterone deficiency, and it does not automatically mean that testosterone therapy is needed. It indicates that further medical assessment may be worthwhile.
The questionnaire is useful because it provides a simple way to start a conversation about symptoms that men might otherwise dismiss as stress, ageing or tiredness. However, several of these symptoms are not specific to low testosterone and may have other explanations.
The review also discusses the AMS (Aging Males’ Symptoms) scale, a longer questionnaire that evaluates psychological, physical and sexual symptoms and their severity. Unlike the shorter ADAM screen, it can help assess the extent of symptoms and changes over time.
Neither questionnaire replaces a clinical assessment and appropriate blood tests. A diagnosis of testosterone deficiency requires symptoms consistent with the condition alongside biochemical evidence of low testosterone.
What the research says about treatment
The review Update on testosterone deficiency and therapeutic options for testosterone replacement therapy examines the evidence for testosterone treatment, including its potential benefits, risks and the importance of selecting the right patients.
For men with confirmed testosterone deficiency, treatment may improve sexual function, body composition, bone mineral density and anaemia in appropriate circumstances. Some men also experience improvements in mood and quality of life. However, the size and consistency of these benefits vary, and treatment should not be viewed as a universal solution for ageing, fatigue or reduced vitality.
The authors also discuss safety concerns surrounding testosterone therapy. Contemporary evidence has helped clarify questions about cardiovascular outcomes and prostate health, but this does not mean that treatment is risk-free. Individual medical history, contraindications, the formulation used and ongoing monitoring all matter.
Possible adverse effects include increased red blood cell concentration, acne, changes in skin or hair, and suppression of sperm production. Monitoring may involve testosterone levels, blood counts, symptom response and other assessments appropriate to the patient.
Treatment should therefore be tailored to a confirmed diagnosis and reviewed over time. If symptoms do not improve despite testosterone levels being corrected, clinicians may need to reassess the diagnosis or investigate other explanations.
For men concerned about fertility, this assessment must also consider whether treatment could reduce sperm production and whether a different strategy would better suit their reproductive goals.
Moving beyond the idea that fertility is only a woman’s concern
Male fertility deserves to be treated as an integral part of reproductive healthcare, not an afterthought. Yet many men seek help only after a couple has experienced difficulty conceiving, or when symptoms such as erectile difficulties, reduced libido or persistent fatigue become hard to ignore.
Greater awareness can help change this. Men should feel able to discuss fertility concerns, seek an assessment and ask how a proposed treatment could affect their chances of having children. They should also understand that fertility and sexual performance are related but distinct: a man may experience erectile difficulties while producing sperm normally, or have impaired sperm production without obvious changes in sexual function.
The work of specialists such as Professor Vaibhav Modgil illustrates the value of looking at male reproductive health as a connected system. His clinical focus on male infertility and andrology, alongside his contribution to research on testosterone deficiency, reflects the importance of accurate diagnosis and treatment decisions that take the whole patient into account.
Ultimately, the goal is not simply to raise a hormone level or improve one symptom. It is to understand what is happening, identify the right treatment and ensure that a man’s wider health—including his plans for fatherhood—remains part of the discussion.
For men experiencing symptoms of testosterone deficiency or difficulty conceiving, the first step is to seek medical advice rather than self-diagnose or start hormone treatment independently. The right assessment can help distinguish between different causes and clarify which options are appropriate.
Research basis: Thompson T, Mubarak M, Jones TH, Pearce I and Modgil V, “Update on testosterone deficiency and therapeutic options for testosterone replacement therapy,” Nature Reviews Urology (2026). https://doi.org/10.1038/s41585-026-01190-3
Editorial note: Medical claims and treatment guidance should be reviewed by a qualified clinician before publication.
